Pacemakers and many other active implants run on an internal battery. Deep, power-hungry and long-lived implants — artificial organs, neural interfaces, implanted pumps — change that calculation: a battery that needs surgical replacement, or a lead through the skin, is a lasting source of risk. Wireless power transfer is the usual answer, and its design space has been reviewed in depth.7
This explainer is for biomedical engineers, research collaborators and clinicians assessing implant programmes. It covers why a single pair of coils struggles with depth and misalignment, what resonance and additional coils change, and which safety limits bound every design.
Why does a single coil pair struggle with depth?
A conventional transcutaneous link is a transformer with an air — and tissue — gap: a transmitter coil outside the body induces a current in a receiver coil inside it. How much power arrives depends on how strongly the two coils are coupled and on the quality factor (Q) of each coil. Coupling depends on geometry. It drops as the separation grows relative to coil size, and it drops again when the coils are offset or tilted.7
Two consequences follow for deep implants. First, efficiency falls as the implant moves away: in a conventional two-coil link the efficiency profile is a monotonically decreasing function of distance.1 Second, the receiver cannot simply be made larger to compensate, because the implant has to fit the anatomy. Ho and colleagues describe how, with near-field coupling limited by rapid field decay, wireless powering beyond superficial depths had required coils at least a centimetre across.2 Patient movement and changes in posture add a third problem: the coupling an engineer designs for on the bench is not the coupling the implant sees every day.
What does resonance change?
If both coils are tuned to the same resonant frequency and have high Q, energy can be exchanged efficiently even when the coupling between them is weak. Kurs and colleagues demonstrated the effect at room scale in 2007: using self-resonant coils in a strongly coupled regime, they transferred 60 W with roughly 40% efficiency over more than 2 m, a distance of up to eight times the coil radius.3 That was not an implant, but it showed that distance need not be fatal if the resonators are good enough.
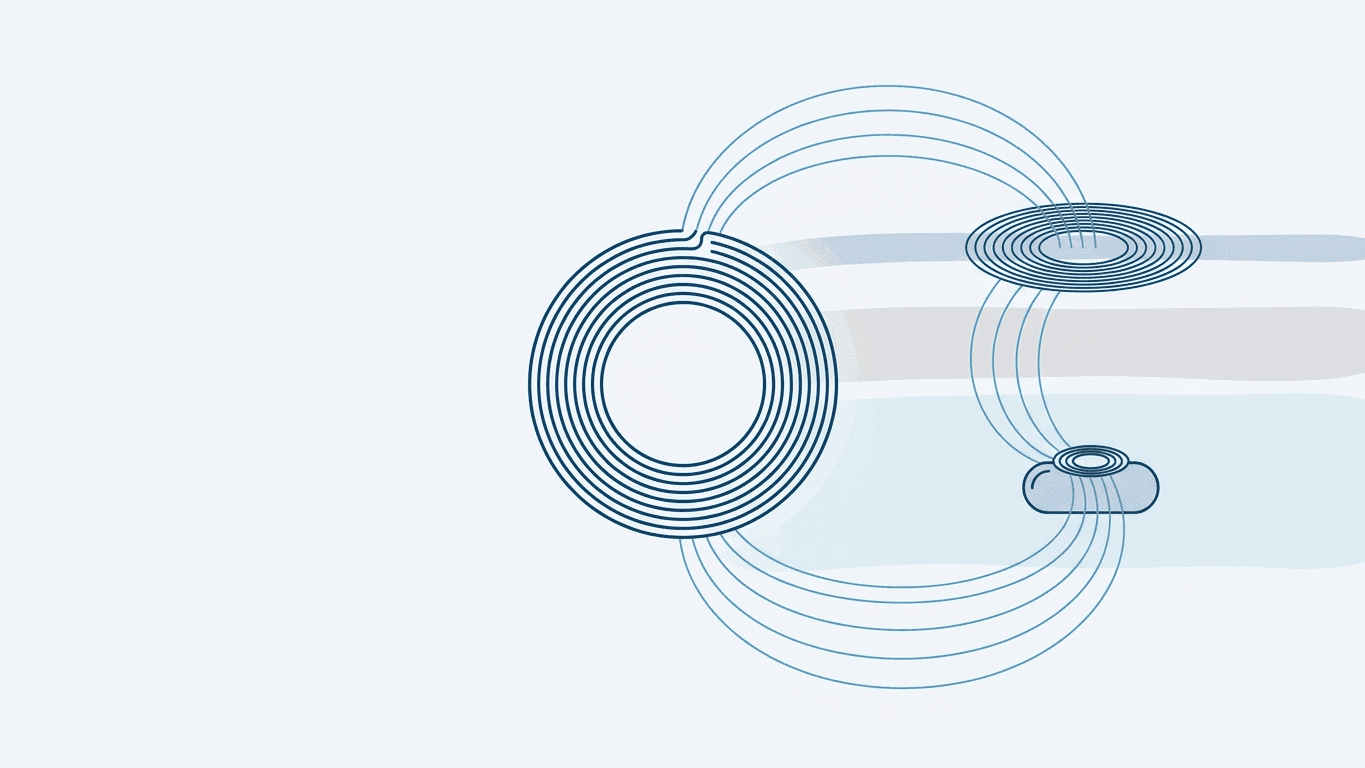
At implant scale, RamRakhyani and colleagues analysed resonance-based four-coil links, in which a driver loop feeds a high-Q transmitter resonator and a high-Q receiver resonator feeds the load loop. In their prototype — 700 kHz, a 22 mm implant coil and a 10–20 mm coil distance — the resonance-based system exceeded 80% efficiency, compared with about 40% for a conventional two-coil link. Just as important, its efficiency did not fall monotonically with distance and was less sensitive to changes in separation.1
Three coils, four coils and relay chains
Adding coils is not automatically better. Kiani and colleagues optimised two-, three- and four-coil links for the same task — 13.56 MHz across a 12 cm gap — and reported power-transfer efficiencies of 15%, 37% and 35% respectively. Efficiency is only half the story: at that distance, the power actually delivered to the load by their three-coil link was 1.5 times that of the two-coil link and 59 times that of the four-coil link. For short distances, they found that two-coil links remained the better choice when high delivered power was needed.4
View chart data
| Category | Power-transfer efficiency |
|---|---|
| Two-coil link | 15 |
| Three-coil link | 37 |
| Four-coil link | 35 |
Optimised designs at 13.56 MHz from a single study, so the conditions are comparable. Efficiency is not delivered power: the four-coil link delivered 59 times less power to the load than the three-coil link.
Source: Kiani, Jow and Ghovanloo, IEEE Trans Biomed Circuits Syst 2011.
A related idea is the relay resonator: a passive, tuned coil placed between transmitter and receiver that picks up energy and passes it on. Zhong, Lee and Hui showed that power can be carried through chains of coil resonators arranged in straight, circular and branched ‘domino’ layouts, including resonators that do not share a common axis.8 For an implant, the attraction is that each hop is shorter than the full path, so each stage operates where coupling is stronger. The cost is that every additional resonator adds loss, must be tuned and must stay where it was placed.
| Architecture | How it works | Strength | Main limitation |
|---|---|---|---|
| Two-coil inductive link | External transmitter coil couples directly to an implanted receiver coil | Simple; high delivered power at short range | Efficiency falls with distance and misalignment |
| Resonant three- or four-coil link | Tuned high-Q resonators added to the transmitter and/or receiver side | Higher efficiency at larger gaps; less sensitive to separation | Delivered power and bandwidth depend on topology; tuning required |
| Relay (intermediate) resonator | A passive tuned coil between transmitter and receiver forwards energy in two or more hops | Each hop is shorter; can route power around geometry | Extra component to implant, tune and keep in position |
| Midfield powering | A patterned plate creates a focused, propagating field in tissue | Millimetre-scale receivers more than 5 cm deep | Milliwatt-level power; more complex transmitter |
Source: RamRakhyani et al. 2011; Kiani et al. 2011; Zhong et al. 2012; Ho et al. 2014.
What limits all of these designs?
Every watt that does not reach the implant is absorbed somewhere — in the coils, in the electronics or in tissue. Two kinds of limit apply.
Temperature rise of the implant
ISO 14708-1, the general standard for active implantable medical devices, sets a thermal safety limit of a 2 °C temperature increase.59 For a wirelessly powered implant, that limit applies to heat from the receiving coil and electronics as well as from any actuator the implant drives. It is the main reason why efficiency, not just delivered power, matters in implant links.
Field exposure in tissue
The ICNIRP 2020 guidelines restrict the general public’s local specific absorption rate (SAR) in the head and torso to 2 W/kg averaged over a 10 g cube, and the whole-body average to 0.08 W/kg, for frequencies from 100 kHz to 6 GHz; below 10 MHz, separate restrictions protect against nerve stimulation.6 ICNIRP explicitly places exposure from medical procedures outside the scope of its guidelines, so for an implant these values are a reference point rather than the device’s regulatory test.6 Ho and colleagues, for example, reported transferring milliwatt-level power to a microimplant more than 5 cm deep with exposure below human safety thresholds.2
How Silicon Life’s two-stage architecture relates
Silicon Life is developing a two-stage magnetic resonance link for its electronically controlled artificial bladder. According to the company, an external transmitter powers a receiving coil fixed under the skin, which acts as a relay and forwards energy to a miniature coil in the device implanted at the bladder. The two stages are designed and tuned as one matched system, with the aim of keeping efficiency and stability as tissue thickness and body position change.10 In the terms used above, it is a relay-resonator architecture with the relay placed subcutaneously.
The same thermal constraint shapes the actuator. The company describes an electromagnet–permanent-magnet valve that switches on a brief pulse and holds its voiding position with the permanent magnet, rather than drawing continuous current; it reports that, in its bench testing, this kept valve heating within 2 °C.10 These are company-reported engineering results, not independently verified or clinical data.
The artificial bladder is investigational. It has not been approved by any regulatory authority and is not available for sale.
Open engineering questions
- Relay stability over years. A subcutaneous relay must stay in position and in tune as tissue heals, encapsulates and changes with weight.
- Variation between patients. Tissue thickness and composition differ widely, so a link must be verified across the range of intended users, not one phantom.
- Efficiency versus delivered power. As the three-coil versus four-coil results show, the most efficient link is not always the one that delivers enough power to the load.4
- Coexistence. Fields from a power link can interfere with other active implants, a risk that exposure guidelines flag but leave to device-specific assessment.6
Frequently asked questions
Is resonant wireless power the same as inductive charging?
Both use magnetic near-field coupling. Resonant links add tuned high-Q resonators so that energy transfers efficiently even when coupling is weak, which extends the useful distance and reduces sensitivity to separation.13
Why not simply increase the transmitter power?
Because the limits are thermal and exposure-based. Power that does not reach the implant heats coils and tissue, and active implants are held to a 2 °C temperature-rise limit.5
Do more coils always mean better performance?
No. Extra coils can raise efficiency at larger gaps, but delivered power, bandwidth and complexity change too; for short gaps a two-coil link can remain optimal.4
Is Silicon Life’s artificial bladder available?
No. It is an investigational programme. Research groups interested in implant power, sensing or signal processing can contact the engineering team.
References
- 1RamRakhyani AK, Mirabbasi S, Chiao M. Design and optimization of resonance-based efficient wireless power delivery systems for biomedical implants. IEEE Trans Biomed Circuits Syst. 2011;5(1):48–63
- 2Ho JS, Yeh AJ, Neofytou E, et al. Wireless power transfer to deep-tissue microimplants. Proc Natl Acad Sci U S A. 2014;111(22):7974–7979
- 3Kurs A, Karalis A, Moffatt R, Joannopoulos JD, Fisher P, Soljačić M. Wireless power transfer via strongly coupled magnetic resonances. Science. 2007;317(5834):83–86
- 4Kiani M, Jow UM, Ghovanloo M. Design and optimization of a 3-coil inductive link for efficient wireless power transmission. IEEE Trans Biomed Circuits Syst. 2011;5(6):579–591
- 5Whalen AJ, Fried SI. Thermal safety considerations for implantable micro-coil design. J Neural Eng. 2023;20(4):046017
- 6International Commission on Non-Ionizing Radiation Protection (ICNIRP). Guidelines for limiting exposure to electromagnetic fields (100 kHz to 300 GHz). Health Phys. 2020;118(5):483–524
- 7Agarwal K, Jegadeesan R, Guo YX, Thakor NV. Wireless power transfer strategies for implantable bioelectronics. IEEE Rev Biomed Eng. 2017;10:136–161
- 8Zhong W, Lee CK, Hui SYR. Wireless power domino-resonator systems with noncoaxial axes and circular structures. IEEE Trans Power Electron. 2012;27(11):4750–4762
- 9ISO 14708-1:2014. Implants for surgery — Active implantable medical devices — Part 1: General requirements for safety, marking and for information to be provided by the manufacturer
- 10Silicon Life. Technology platform: two-stage magnetic resonance wireless power (company description and bench results)
Silicon Life. Powering deep implants: how resonant coupling and relay coils extend wireless power. SILICON·LIFE Insights. 11 October 2026.

Silicon Life develops urological devices and implantable systems in Wuhan, China. Its Insights are written for healthcare professionals, with the sources for each article listed in full.
This article is provided for educational purposes for healthcare professionals. It does not constitute medical advice and does not replace the Instructions for Use of any device. Product availability and indications differ by country.
New articles on urology devices and implant engineering.
Clinical reviews, engineering notes and company news from Silicon Life, sent when new articles are published.
Occasional emails. Unsubscribe at any time.